
 María Victoria Galarza Coellar
Abstract
This exploratory pilot study developed and validated a digital platform integrating Ecological Momentary Assessment (EMA) to support therapeutic follow-up and patient adherence in psychotherapy. Using an exploratory-descriptive mixed-methods design, the project followed four stages: analysis, design, development, and pilot validation. The resulting ecosystem included a mobile application for patient self-monitoring and a web-based clinical dashboard for therapists, supported by secure cloud infrastructure. The platform enables daily EMA logging through emotional and behavioral questions, guided grounding exercises, automated alerts for critical emotional indicators, and real-time visualizations to support clinical decision-making. Pilot validation involved eight volunteers, including four patients and four therapists. System Usability Scale (SUS) results indicated high perceived usability, with scores of 89.38 (SD = 6.57) for the mobile application and 88.12 (SD = 11.25) for the clinical dashboard, both within the excellent range. Qualitative feedback highlighted the usefulness of emotional trend visualizations, timely alerts, and role-based data access. These preliminary findings suggest that EMA-based digital platforms may enhance patient engagement and provide therapists with actionable information for more responsive care. Further longitudinal studies are needed to evaluate clinical effectiveness and scalability.
Resumen
Este estudio piloto exploratorio desarrolló y validó una plataforma digital que integra Evaluación Ecológica Momentánea (EMA) para apoyar el seguimiento terapéutico y la adherencia del paciente en psicoterapia. Mediante un diseño exploratorio-descriptivo con enfoque mixto, el proyecto siguió cuatro etapas: análisis, diseño, desarrollo y validación piloto. El ecosistema resultante incluyó una aplicación móvil para el automonitoreo del paciente y un panel clínico web para terapeutas, respaldados por una infraestructura segura en la nube. La plataforma permite el registro diario de EMA mediante preguntas emocionales y conductuales, ejercicios guiados de grounding, alertas automatizadas ante indicadores emocionales críticos y visualizaciones en tiempo real para apoyar la toma de decisiones clínicas. La validación piloto incluyó ocho voluntarios: cuatro pacientes y cuatro terapeutas. Los resultados de la Escala de Usabilidad del Sistema (SUS) indicaron una alta usabilidad percibida, con puntajes de 89.38 (DE = 6.57) para la aplicación móvil y 88.12 (DE = 11.25) para el panel clínico, ambos dentro del rango excelente. La retroalimentación cualitativa destacó la utilidad de las visualizaciones de tendencias emocionales, las alertas oportunas y el acceso a datos basado en roles. Estos hallazgos preliminares sugieren que las plataformas digitales basadas en EMA pueden fortalecer el compromiso del paciente y proporcionar a los terapeutas información accionable para una atención más oportuna. Se requieren estudios longitudinales posteriores para evaluar su efectividad clínica y escalabilidad.
Keywords
Ecological Momentary Assessment; mHealth; digital mental health; psychotherapy adherence; clinical dashboard; usability evaluation.
Palabras clave
Evaluación Ecológica Momentánea; mHealth; salud mental digital; adherencia psicoterapéutica; panel clínico; evaluación de usabilidad.
Artículo recibido: 30-mar-26. Artículo aceptado: 22-may-26.
DOI: 10.33324/uv.vi88.1165 Páginas: 168-193
1.
Introduction
Digital technologies have significantly transformed mental health care delivery, particularly following the COVID-19 pandemic (Philippe et al., 2022). In this context, Ecological Momentary Assessment (EMA) emerges as a validated methodology for recording emotional and behavioral states in real time within users’ natural environments (Stone & Shiffman, 1994), reducing memory bias and enhancing ecological validity. However, a critical gap persists between commercially available wellness applications and clinically rigorous solutions that integrate EMA with evidence-based therapeutic frameworks such as Cognitive Behavioral Therapy (CBT), robust privacy protections, and user-centered design principles.
In Latin America, while EMA implementation exists in Argentina (Meglio et al., 2022), Chile (Inostroza et al., 2024), and Colombia (Castillo Zárate, 2022), substantial barriers to digital mental health access remain unaddressed. In Ecuador specifically, mental health services face critical infrastructure challenges: limited availability of trained psychotherapists in rural and underserved communities, high-cost barriers to individual psychotherapy, and inadequate integration of technology-enabled monitoring into routine clinical care. Additionally, digital mental health solutions designed in developed-country contexts often lack cultural and linguistic localization relevant to Ecuadorian populations, creating further access inequities. The absence of affordable, evidence-based digital platforms adapted to local healthcare realities represents a significant unmet clinical need, particularly for continuous therapeutic monitoring and therapist-patient communication in resource-limited settings. This gap creates a research opportunity to develop a scalable, culturally appropriate solution bridging evidence-based psychotherapeutic interventions and practical digital tools accessible to diverse Ecuadorian populations.
This investigation addresses three fundamental clinical and methodological questions: How can a digital platform systematically capture valid EMA data while minimizing patient burden and integrating assessment into daily routines? How can patient data be visualized to support clinically meaningful therapist decision-making while protecting privacy and maintaining assessment validity? What design and implementation strategies ensure the platform’s feasibility and acceptability for both patients and therapists in the Ecuadorian healthcare context?
This investigation is grounded in multiple scientifically validated theoretical frameworks. First, Ecological Momentary Assessment (Ebner-Priemer & Trull, 2009; Trull & Ebner-Priemer, 2014) captures intraindividual emotional variability with precision, overcoming memory biases inherent in retrospective assessment. Second, Ecological Momentary Interventions (Castilla et al., 2022) provide real-time therapeutic support through evidence-based techniques, such as sensory grounding exercises, that are automatically activated when critical emotional states are detected. Third, the BIT Model (Mohr et al., 2014) and Internet Intervention Model (Ritterband et al., 2009) provide frameworks for integrating clinical objectives, behavioral change strategies, and user-adapted workflows into digital interventions. Fourth, therapeutic adherence research (Christensen et al., 2009; Wenze & Miller, 2010) emphasizes immediate feedback, frequent follow-ups, and visual mechanisms as critical engagement facilitators. Finally, User-Centered Design principles (Saparamadu et al., 2021) ensure platform usability, accessibility, and clinical utility for both patients and therapists.
International evidence supports EMA-based digital interventions. Colombo et al. (2019) demonstrated through systematic review that EMA accurately captures emotional variability in depression with high precision. Ben-Zeev et al. (2015) emphasize that sustained adherence in mobile mental health interventions requires multidisciplinary design, cultural adaptability, and minimal user friction. Aguilera & Muench (2012) stress that integrating CBT into mobile applications requires active therapist involvement and adaptation to mobile modalities. Mengelkoch et al. (2023) validate EMA’s effectiveness for monitoring psychologically meaningful variables such as mood, stress, and social interaction, demonstrating that real-time assessment prevents retrospective bias.
The general objective is to develop and validate a digital platform integrating EMA to improve therapeutic follow-up and patient adherence by collecting real-time data on emotional states and behavioral patterns. Specific objectives include: investigating EMA’s theoretical and clinical foundations; conducting requirements elicitation with clinical experts and benchmarking existing solutions; designing a functional architecture incorporating usability, privacy, and evidence-based engagement principles; developing a prototype with EMA capture, therapeutic interventions, and clinical dashboards; and conducting usability validation with patients and therapists. Expected contributions include: a clinically meaningful design operationalizing EMA with minimal patient burden; preliminary evidence of high perceived usability; and a scalable, culturally relevant solution for Ecuador and the Andean region demonstrating the viability of integrating evidence-based psychotherapy, EMA, and user-centered design.
2.
Methods
This study employed an exploratory-descriptive mixed-methods design, combining a detailed characterization of the phenomenon under study with qualitative and quantitative data collection during the validation phase. The research was structured in four iterative phases: Analysis, Design, Development, and Feedback. Participants were recruited through purposive sampling and included eight volunteers (four patients and four therapists) selected based on availability and interest in participating in the pilot test. Patients were required to have active engagement with a mental health treatment, while therapists needed at least one year of clinical experience and familiarity with digital health tools. Participation was voluntary with informed consent, and all responses were collected anonymously for research and product improvement purposes only.
Analysis Phase
A systematic literature review was conducted using PubMed and Scopus databases with search keywords including “ecological momentary assessment,” “digital psychotherapy,” “cognitive behavioral therapy mobile applications,” and “adherence in e-health.” The review examined foundational research establishing EMA as a validated real-time assessment methodology that reduces memory bias compared to retrospective reporting (Stone & Shiffman, 1994) and effectively captures intraindividual variations in emotional and behavioral states with enhanced ecological validity (Ebner-Priemer & Trull, 2009). This review informed the theoretical framework and clinical rationale for the platform’s design.
A comparative analysis of existing digital mental health applications (Headspace, Woebot, Moodfit) was conducted to identify best practices, limitations, and design elements relevant to EMA-based interventions. Applications were evaluated across intervention type, primary functionalities, identified limitations, and design features to understand the current landscape and inform differentiation of the proposed platform.
Expert consultation was conducted with four clinical psychology professionals experienced in psychotherapy and familiar with digital health tools. Exploratory interviews explored clinical priorities for real-time patient monitoring, data visualization needs, workflow integration requirements, and privacy/security expectations. Findings from literature review, benchmarking analysis, and expert consultation were synthesized to establish the clinical and functional foundation for subsequent design and development phases.
Design Phase
User interface prototypes were developed following User-Centered Design (UCD) principles (Saparamadu et al., 2021) and Norman’s design heuristics (Norman, 1988), emphasizing system state visibility, consistency, user control, mental models, and error prevention. Visual design incorporated color psychology principles with warm tones (terracotta and orange), conveying warmth and motivation, and strategic alert colors (red), communicating clinical urgency (Kaya & Epps, 2004). Typography prioritized modern sans-serif fonts for mobile legibility, with careful color contrast selection following W3C inclusive design standards for accessibility. A friendly avatar was integrated as an interaction guide to humanize the experience and enhance user trust (Morris et al., 2018). Information architecture for the therapist dashboard employed hierarchical organization with progressive disclosure, following information visualization principles of “overview first, zoom and filter, then details-on-demand” (Shneiderman, 2025) to facilitate clinical decision-making with large volumes of data.
Design specifications incorporated clinical priorities identified during expert consultation: real-time EMA data capture with minimal patient burden, accessible visualizations supporting therapist interpretation of emotional patterns, and transparent role-based data access. Evidence-based engagement mechanisms, including motivational feedback, progress visualization (streaks and graphs), and guided therapeutic exercises, were integrated to support treatment adherence (Christensen et al., 2009; Wenze & Miller, 2010). The design emphasized security and privacy protection of sensitive mental health information through explicit access controls and data confidentiality measures (Mohr et al., 2013).
Development Phase
The platform was developed using agile methodologies with iterative cycles to ensure continuous quality improvement (Mendoza, 2020). A mobile application was created to enable patients to register, authenticate, respond to daily EMA questionnaires, view personalized emotional trend graphs, access self-reported statistics, and engage in guided grounding exercises. A web-based clinical dashboard was designed for therapists to securely access patient information through role-based authentication, visualize individual patient EMA responses and emotional patterns over time, review automatically generated clinical alerts based on concerning emotional indicators, manage patient caseloads with filtering and search functionality, and export data for clinical record-keeping. Both applications are integrated with cloud-based backend services to ensure data persistence, real-time synchronization, automated alert generation based on clinical thresholds, and secure authentication mechanisms. The platform prioritized user experience, data security, and clinical utility throughout development. Technical implementation details and code repositories are available upon request or through open-access documentation.
Feedback Phase
This pilot validation study was conducted according to ethical principles for research with human subjects, including respect for persons, beneficence, and justice (Belmont Report principles). All participants provided written informed consent prior to participation, with a clear explanation of: study purpose and procedures, data collection methods, voluntary nature of participation, right to withdraw at any time without penalty, data confidentiality and storage practices, and intended uses of findings. The study protocol was reviewed and approved by institutional ethics oversight to ensure protection of vulnerable populations (patients receiving mental health treatment). All participants were assured that their clinical care would not be affected by participation decisions or responses provided. Compensation was offered to participants to acknowledge the time investment required for pilot testing.
Pilot validation employed a mixed-methods methodological approach with a structured evaluation protocol combining quantitative and qualitative data collection. Participants were intentionally selected according to the role they evaluated within the platform. The patient-side mobile application was assessed by psychology students from Universidad del Azuay, whose academic background allowed them to interact with the EMA-based self-monitoring functions from a psychologically informed user perspective. The therapist dashboard was evaluated by clinical psychologists affiliated with UDA Salud, who provided feedback based on their professional experience in clinical assessment, patient follow-up, and therapeutic decision-making. This participant profile was considered relevant for interpreting score variability, since students and practicing clinicians may differ in prior exposure to digital health tools, clinical experience, expectations regarding usability, and familiarity with therapeutic monitoring processes.
Data collection instruments included: (1) the System Usability Scale (SUS), a validated ten-item questionnaire with five-point Likert scale (1=strongly disagree; 5=strongly agree) measuring perceived usability, utility, engagement, and clinical impact (Bangor, 2009); and (2) open-ended interview questions capturing qualitative feedback on design strengths, usability friction points, improvement suggestions, clinical visualization utility, and user experience. Prior to assessment, each participant completed a standardized set of guided tasks to ensure comparable minimal platform familiarity. Therapist tasks included: filtering patient data by date ranges, reviewing mood versus stress visualizations, reviewing clinical alerts, exporting clinical data, and linking new patients. Patient tasks included: account registration and authentication, completing daily EMA questionnaires, viewing personalized emotional trend graphs and statistics, adjusting temporal filters, and engaging in guided grounding exercises.
SUS scoring followed the standard validated procedure: subtracting 1 from odd-numbered items, calculating (5 − response) for even-numbered items, summing the ten values (range 0–40), and multiplying by 2.5 to obtain a total score (0–100). Interpretation referenced established SUS guidelines (≥80.3 = Excellent; 68–80.2 = Good; 55–67.9 = Acceptable; 45–54.9 = Poor; <45 = Deficient), with 68 as the reference usability benchmark (Bangor, 2009). Quantitative data were analyzed descriptively through mean, standard deviation, and 95% confidence intervals to characterize perceived usability. Item-level analysis identified patterns in ease of learning, perceived consistency, integration of functionality, and user confidence. Qualitative data from open-ended responses were analyzed through inductive thematic coding to identify recurrent themes related to usability strengths, design limitations, clinical utility perceptions, and recommended improvements. The integration of quantitative usability scores and qualitative thematic findings allowed for a complementary interpretation of platform performance and user experience. Data analysis was conducted using spreadsheet software for quantitative summary and qualitative synthesis. All personal identifiers were removed from data during storage and analysis; participants are identified only by role (patient/therapist) and numerical identifiers. Data is maintained in secure storage with restricted access.
3.
Results
3.1 Comparative Analysis and Benchmarking
A benchmarking analysis of digital mental health applications (Headspace, Woebot, Moodfit) was conducted to identify best practices, limitations, and differentiating elements. The analysis revealed that while commercial applications offer psychoeducational resources and support, they lack real-time emotional state registration, personalized clinical feedback, and immediate reinforcement mechanisms, limiting long-term adherence. In contrast, the proposed MindBloom platform integrates daily EMA recording, a specialized therapist dashboard, automatic feedback, and a grounding module, enabling unified patient self-assessment and clinical supervision within a single ecosystem.
Table 1
Benchmarking of Digital Mental Health Applications. Comparison of functionalities, limitations, and differentiating elements between existing applications (Headspace, Woebot, Moodfit) and the proposed MindBloom platform.

3.2 Functional and Non-Functional Requirements
Through exploratory consultations with clinical psychology experts (n=4), functional and non-functional requirements were identified and prioritized using the MoSCoW framework (Must/Should/Could/Won’t). For the patient application, critical requirements included EMA questionnaire capture with low friction, visual progress feedback (graphs and streaks), appointment reminders, secure linking with a therapist by code, and grounding exercise modules. For the therapist dashboard, essential requirements included patient management, visualization of EMA responses by patient and time period, automatic clinical alerts based on risk patterns, and data export to CSV. Non-functional requirements across both components emphasized usability (SUS greater than or equal to 68), accessibility (W3C standards), performance (sub-second response times), and security (role-based access control, encryption, and immutable audit trails).
Table 2
Functional and Non-Functional Requirements - Patient Application. Priority levels (Must/Should/Could/Won’t) for EMA capture, progress visualization, reminders, security, and gamification elements.

Table 3
Functional and Non-Functional Requirements - Therapist Dashboard. Priority levels (Must/Should/Could/Won’t) for patient management, EMA visualization, alerts, and data export functionality.

3.3 System Architecture and Data Flow
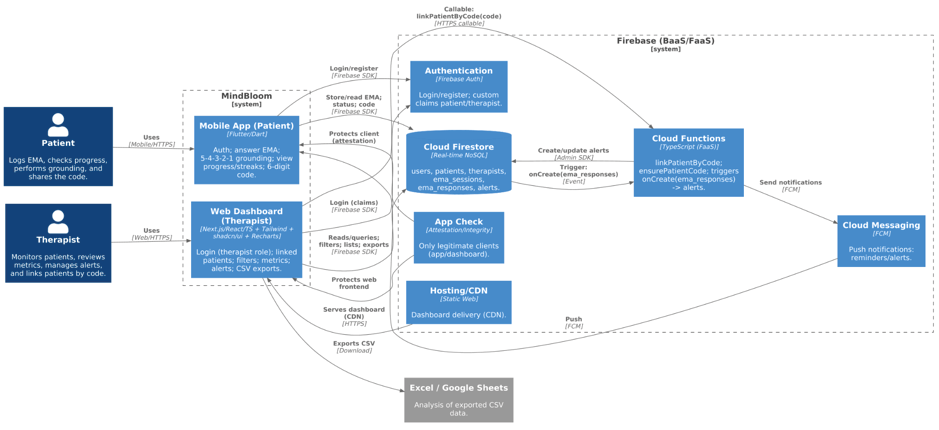
The system was architected as client-server, cloud-native, serverless, and event-driven, organized as a monorepo integrating the mobile application (Flutter/Dart), web dashboard (Next.js/React/TypeScript), and Firebase backend services. The architecture enforces separation of concerns: patients interact with the mobile app to authenticate, respond to daily EMA questionnaires, and view personalized progress statistics; therapists access the web dashboard to manage assigned patients, visualize EMA response patterns, and monitor automatically generated clinical alerts. Patient-therapist links are established via secure code-based linking and enforced through role-based Firestore security rules, implementing the principle of least privilege and mutual data visibility restrictions.
Figure 1
C4 Context Diagram of MindBloom System. Illustrates the system boundary, human actors (Patient, Therapist), external dependencies (Firebase BaaS/FaaS), and high-level interaction flows. Format: JPG/TIFF, 20cmx30cm, 300 dpi.
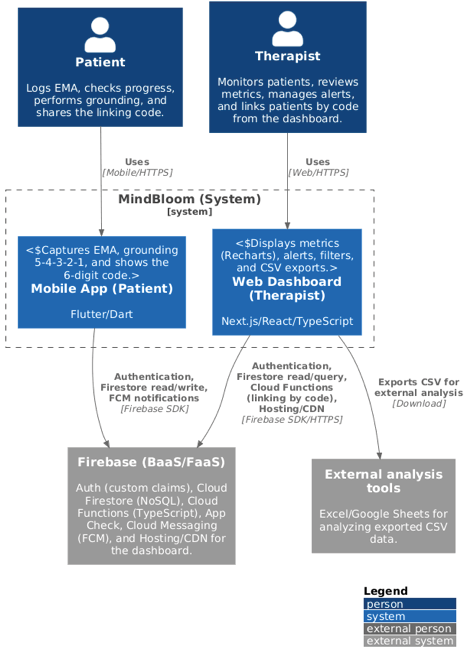
Figure 2
C4 Container Diagram of MindBloom System. Details executable components: mobile app, web dashboard, Firebase services (Auth, Firestore, Cloud Functions, App Check), and their interactions. Format: JPG/TIFF, 20cmx30cm, 300 dpi.
3.4 Database Design and Data Model
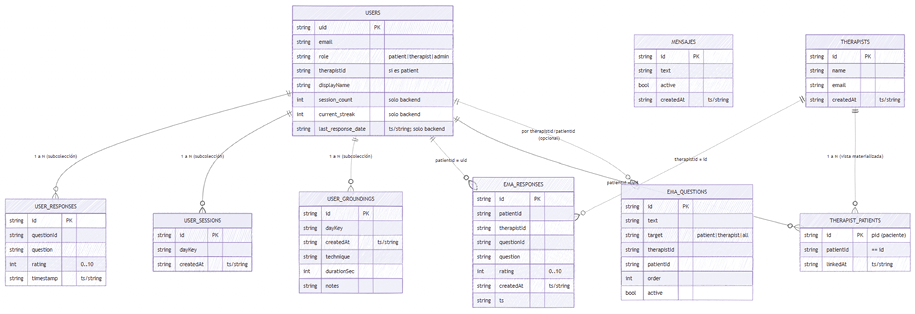
The database was designed as a NoSQL document model in Cloud Firestore, organizing information around users and clinical EMA/grounding records using root collections and subcollections reflecting ownership and clinical supervision relationships. The core users/{uid} collection identifies each user (patient or therapist) with role assignment. Three owner-only subcollections store: responses (EMA response history), sessions (daily streaks with dayKey and createdAt), and groundings (grounding session metadata). At the root level, ema_responses concentrates system-wide EMA data with minimal fields for analysis and linking (patientId, therapistId, questionId, question, rating 0-10, createdAt), optimizing therapist dashboard queries and exports. Security and audit integrity are maintained through: role-based Firestore rules restricting read/write by role and patient-therapist link; immutability of records once created (no client-side updates); audit fields (createdAt, updatedAt, createdBy) on all documents; and server-maintained fields (session_count, current_streak, last_response_date) updated exclusively via Cloud Functions with Admin SDK.
Figure 3
Firestore NoSQL Document Data Model. Shows root collections (users, ema_responses, ema_questions, messages, therapists) and subcollections with field types, cardinality (1:N relationships), audit fields, and server-maintained fields. Format: JPG/TIFF, 20cmx30cm, 300 dpi, or EPS/AI diagram.
3.5 User Interface and Experience Design
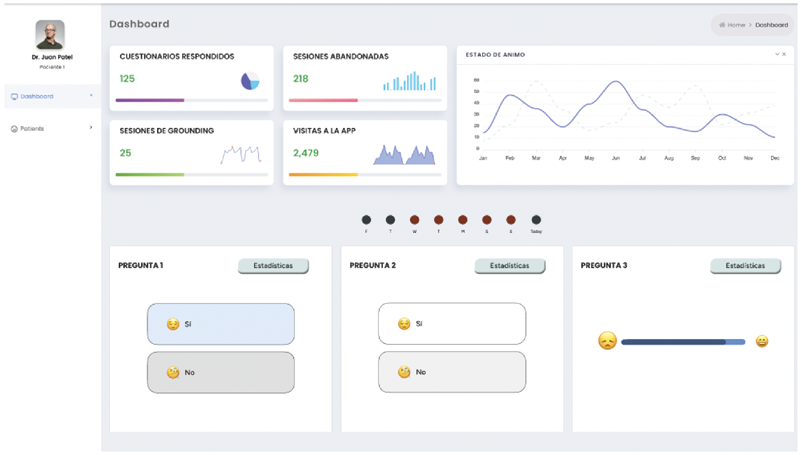
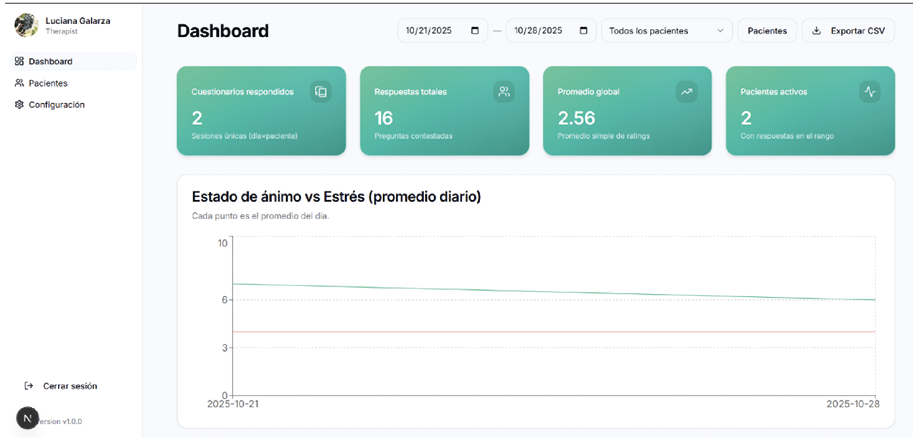
High-fidelity prototypes were developed in Figma following User-Centered Design (UCD) principles and Norman’s design heuristics. Visual design incorporated color psychology: soft, warm tones (terracotta and orange) to convey warmth, trust, and motivation; bright, alert colors (red) for clinical risks. Typography prioritized modern sans-serif (Roboto) for mobile legibility and accessibility. A friendly, gradient-based avatar was integrated as an interaction guide to humanize the experience. The patient application presents screens for user registration/login, daily EMA questionnaire flow with low cognitive load, real-time progress visualization (graphs, streaks, averages), and interactive grounding sessions. The therapist dashboard employs hierarchical information organization with progressive disclosure following information visualization best practices, featuring patient management, EMA response charts with temporal and patient-level filters, automatic clinical alerts, and CSV export functionality.
Figure 4
Patient Mobile Application UI Screens (Figma Prototypes). Key screens: (a) Welcome/Login, (b) Therapist linking code, (c) Daily EMA questionnaire, (d) Progress graphs, (e) Grounding session, (f) User profile with statistics. Format: JPG/TIFF composite, 20cmx30cm, 300 dpi.
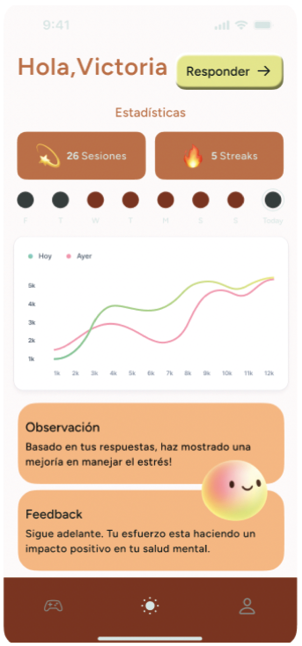
Figure 5
Therapist Dashboard Web UI (Figma Prototypes). Key screens: (a) Therapist login, (b) Patient management panel, (c) Overview dashboard with EMA charts and alerts, (d) Patient-specific detail view with filters, (e) Alert panel, (f) CSV export preview. Format: JPG/TIFF composite, 20cmx30cm, 300 dpi.
3.6 Implementation Results and System Integration
The development phase produced a fully functional ecosystem in the development environment: the patient mobile application (Flutter/Dart) achieved an executable APK for Android testing; the therapist web dashboard (Next.js/React/TypeScript) operated in local development mode with live Firebase integration. Key implemented functionalities include: patient registration and authentication with role-based access; therapist dashboard access with role verification and patient assignment by secure 6-digit code; daily EMA questionnaire capture with real-time persistence to Firestore and automatic trigger-based alert generation; visual progress display (graphs, daily streaks, period averages); interactive grounding exercise modules; user profile management; and data export to CSV format. Security implementation verified: role-based Firestore rules enforcing patient-therapist relationships; immutable client-side data (no edit/delete post-creation); server-maintained metrics (streaks, session counts) updated exclusively via Cloud Functions; Firebase App Check restricting interactions to legitimate applications. The monorepo structure facilitated code reuse, consistent styling, and synchronized backend integration.
Figure 6
Patient Application Implementation Screenshots. Development environment evidence showing: (a) User registration/login, (b) Therapist code linking, (c) Daily EMA questionnaire, (d) Progress dashboard with graphs, (e) Grounding session, (f) User statistics panel. Format: JPG/TIFF, screen resolution or higher.
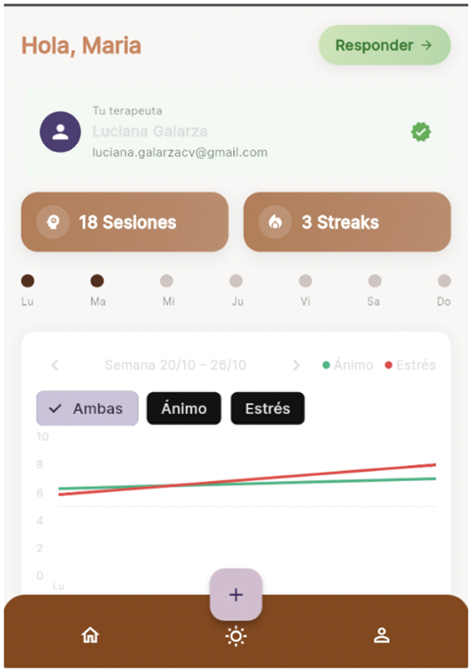
Figure 7
Therapist Dashboard Implementation Screenshots. Development environment evidence showing: (a) Therapist login, (b) Patient management panel, (c) Overview dashboard with EMA visualizations, (d) Patient-specific detail view with filters, (e) Clinical alerts panel, (f) CSV export functionality. Format: JPG/TIFF, screen resolution or higher.
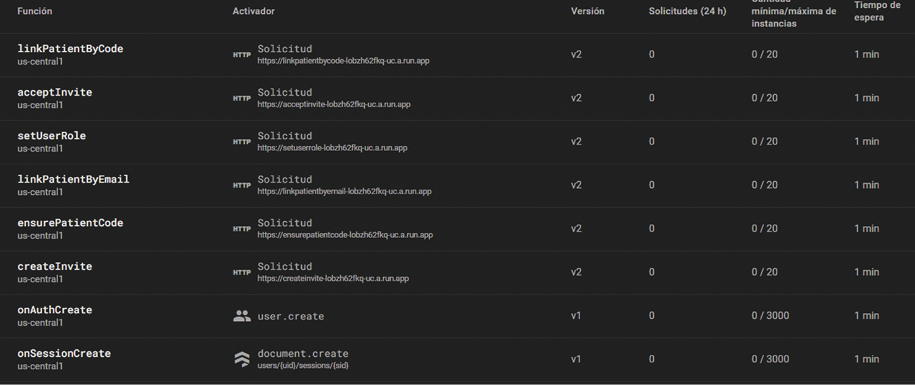
Figure 8
Firebase Development Console. Shows Cloud Firestore collections, Cloud Functions deployment, authentication user records, and security rules configuration. Demonstrates backend infrastructure supporting the MindBloom ecosystem. Format: JPG/TIFF screenshot.
3.7 Pilot Validation Results - System Usability Scale (SUS)
The pilot validation was conducted with eight volunteer participants (n=4 patients, n=4 therapists). For the patient application, the mean SUS score was 89.38 (SD=6.57; 95% CI=[82.93, 95.82]), placing the app in the “Excellent” category (greater than or equal to 80.3) and well above the reference usability average of 68. The narrow confidence interval indicates consistent positive perceptions across the sample. For the therapist dashboard, the mean SUS score was 88.12 (SD=11.25; 95% CI=[77.10, 99.15]), also within the “Excellent” category. Both scores provide preliminary evidence of high perceived usability. Descriptive analysis of individual SUS items identified particular strengths in consistency of interface language and integration of core functions. Score variation in the therapist group reflects heterogeneous prior technology experience, expected in clinical populations.
Table 4
System Usability Scale (SUS) Results - Patient Application (n=4). Individual respondent scores, descriptive statistics (Mean, SD, 95% CI), and SUS category rating (Excellent). Format: Excel or JPG/TIFF at 300 dpi.
|
n |
Mean SUS |
ST |
95% CI lower |
95% CI upper |
Adjective rating |
|
4 |
89.38 |
6.57 |
82.93 |
95.82 |
Excellent (A) |
Table 5
System Usability Scale (SUS) Results - Therapist Dashboard (n=4). Individual respondent scores, descriptive statistics (Mean, SD, 95% CI), and SUS category rating (Excellent). Format: Excel or JPG/TIFF at 300 dpi.

3.8 Qualitative Feedback and User Experience Themes
Qualitative analysis of open-ended responses revealed consistent themes. Strengths identified by patients included: clarity and directness of EMA design, rapid completion with low cognitive load, comprehensible therapist linking code, and intuitive access to statistics supporting self-reflection. Friction points were minimal and included: initial uncertainty about EMA scale interpretation, desire for explicit onboarding guidance, and preference for more visible confirmation messages upon task completion. For the therapist dashboard, strengths included: clear hierarchical organization facilitating exploration from overview to details, effective filtering, and the utility of CSV export. Friction points included: initial uncertainty about the recommended workflow and some nomenclature misalignment with clinical language conventions. Both groups suggested: brief onboarding content, preset date ranges (7/14/30 days) to reduce filtering steps, and standardized CSV headers for easier downstream analysis.
3.9 Summary of Key Findings
The results demonstrate that the MindBloom platform successfully operationalizes Ecological Momentary Assessment (EMA) with integrated clinical supervision, responsive user interface design, and robust security architecture. Benchmarking analysis confirmed a market gap addressed by the proposed solution: combining validated EMA methodology with therapist oversight and real-time feedback mechanisms. The requirements analysis identified critical functionalities for patient adherence and therapist decision-making. The technical architecture—cloud-native, serverless, and event-driven—provides scalability and operational efficiency while maintaining strict data confidentiality through role-based access control and immutable audit trails. Pilot validation via SUS confirms high perceived usability (Patient App: 89.38/100, Therapist Dashboard: 88.12/100), indicating that design decisions effectively integrate psychological principles, information visualization best practices, and clinical workflow requirements. Qualitative feedback highlights alignment with users’ mental models and identifies targeted areas for improvement (onboarding, terminology, preset filters) for future iterations. While results are preliminary (small sample, development environment), they provide evidence that the proposed platform approach is technically viable and meets user expectations for both patient and clinical populations.
4.
Discussion and Conclusions
4.1 Discussion
Usability assessment via System Usability Scale (SUS) revealed high scores for both the patient application (89.38) and therapist dashboard (88.12), with n=4 per role. These values substantially exceed the historical average benchmark of approximately 68 and fall within the “Excellent” category according to standard SUS interpretive frameworks (Bangor, 2009), providing a robust comparative context for pilot-phase user perception. From a substantive perspective, the convergence of ease of learning, perceived consistency, and low friction in critical workflows (login, EMA registration, trend visualization for patients; code-based linking, filtering, and export for therapists) suggests that design decisions grounded in User-Centered Design (UCD) (Saparamadu et al., 2021), Norman’s heuristics (Norman, 1988), and hierarchical information organization were successfully translated into interactions aligned with project expectations, without implying clinical efficacy.
The high usability finding is consistent with the literature on digital mental health interventions and information visualization. Frameworks such as the BIT Model (Behavioral Intervention Technology) structure the “why, how, what, how-technical, and when” dimensions of interventions, reducing perceived complexity and coordinating components (notifications, records, feedback) to minimize cognitive load during task completion (Mohr et al., 2014). Complementarily, the Internet Intervention Model emphasizes usability, visual design, personalization, and reinforcement as facilitators of therapeutic adherence and effective module progression (Ritterband et al., 2009). In the MindBloom platform, dashboard panels, filters, and microinteractions such as the avatar (Morris et al., 2018), confirmation messages, and real-time feedback align with these recommendations, evidencing a system functionally coherent with psychological therapy principles. However, causal impact on clinical outcomes requires evaluation in larger samples with longitudinal designs.
Regarding Ecological Momentary Assessment, the convergence between strong usability metrics and in-situ, real-time sampling aligns with extensively documented methodological benefits: reduced memory bias, enhanced ecological validity, and increased sensitivity to intraindividual variability (Stone & Shiffman, 1994; Ebner-Priemer & Trull, 2009). The literature on Experience Sampling Method (ESM)/EMA in mobile health indicates that smartphones are optimal platforms for integrating brief self-reports, sensors, and contextual information, enabling capture of daily dynamics clinically relevant for reasoning and decision-making (van Os et al., 2017). Furthermore, the validity of EMA for monitoring psychologically meaningful variables—including mood, stress, energy, mindfulness, and social interaction—has been demonstrated in diverse populations (Mengelkoch et al., 2023). The combination of brief prompts, trend visualizations, and lightweight reinforcement mechanics in MindBloom aligns with these guidelines, suggesting substantial potential for real-world effectiveness post-launch.
External evidence further supports the interaction design choices adopted. Reviews and mHealth studies emphasize that modular content delivery, brief and frequent interactions, reminders, and immediate feedback align better with natural usage patterns than traditional session-based formats (Muñoz, 2010). Positive effects have been reported across diverse technological approaches—for instance, virtual reality as a complementary tool in specific contexts (Garcia-Palacios et al., 2015)—suggesting an integrative horizon for future platform iterations combining passive monitoring (EMA) with active intervention (Ecological Momentary Interventions; Castilla et al., 2022), while maintaining ethical and privacy standards essential to clinical environments (Mohr et al., 2013). Ben-Zeev et al. (2015) underscore the importance of multidisciplinary design, cultural adaptability, and low friction for sustained mobile intervention adherence, all addressed in the present platform. Additionally, adherence to therapeutic digital interventions is strengthened by immediate feedback, visual reinforcement (graphs, streaks), and engagement mechanisms (Christensen et al., 2009; Wenze & Miller, 2010), all integrated in the MindBloom design.
However, critical limitations must be acknowledged. First, the reduced sample size (n=4 per role) mandates caution when extrapolating SUS scores and broadens estimation uncertainty; although observed values are high, their precision is limited. Second, testing occurred in a development environment rather than production, excluding assessment of realistic load conditions, device heterogeneity, network latencies, and longitudinal adherence patterns. Third, SUS is a global perception measure that does not pinpoint specific friction sources (microcopy, latencies, affordances), suggesting the need for complementary metrics such as task completion times, error rates, success frequencies, user experience scales, and task-level analysis. Colombo et al. (2019) note that such limitations are not atypical in mental health technology pilots, where measurement reactivity is low but not negligible and requires context-specific monitoring. Additionally, generalization to diverse clinical populations necessitates designs addressing accessibility, cultural and linguistic localization, and clinical support (Mohr et al., 2013), as emphasized in regional studies exploring EMA viability in Latin America (Meglio et al., 2022; Inostroza et al., 2024; Castillo Zárate, 2022).
In addition, one relevant consideration arising from the pilot validation concerns the interpretive uncertainty of EMA scores and the need for further refinement of clinical terminology within the platform. Since the current version uses preliminary emotional and behavioral indicators, EMA responses should be understood as self-reported signals that support therapeutic follow-up rather than as diagnostic measures. Future iterations of the tool will refine the EMA interpretation scales by incorporating clinically validated thresholds, clearer score ranges, and therapist-adjustable alert criteria. Additionally, the clinical terminology used in the platform will be reviewed with mental health professionals to ensure conceptual precision, avoid diagnostic overstatement, and align the language of the system with established psychological practice. These refinements are expected to improve the clinical interpretability of the data and strengthen the platform’s usefulness as a complementary tool for psychotherapy.
Clear research and improvement directions emerge from this analysis. First, replication with larger and heterogeneous samples across therapist subspecialties and patient profiles is necessary to estimate usability variability and validate the preliminary findings in diverse contexts. Second, longitudinal studies correlating EMA patterns with adherence and intermediate clinical outcomes (mood/stress trends) while controlling for reactivity would consolidate clinical utility, consistent with EMA’s capability to capture intraindividual variability (Trull & Ebner-Priemer, 2014). Third, production-environment testing of performance and accessibility metrics following W3C accessibility standards would quantify real-world failure rates and access control coverage. Fourth, low-cost, high-impact UX refinements anticipated by qualitative feedback—such as lightweight onboarding, standardized exports, and empty states—should be iteratively implemented following User-Centered Design principles. Finally, cross-cultural validation in Latin American settings would address documented gaps in digital mental health accessibility and provide evidence of contextual relevance, particularly important given the limited availability of validated digital mental health tools in the region (Philippe et al., 2022).
In synthesis, the discussion indicates that a user-centered platform integrating EMA with cloud-managed architecture (Nyabuto, 2024; Kratzke & Quint, 2017; Khriji et al., 2022) and explicit security controls (Hu, 2024) can achieve high perceived usability and generate clinically relevant data for real-world decision-making. The technical implementation leveraging serverless databases (Cloud Firestore, 2025), event-driven architecture, and role-based access control (Mohr et al., 2013) demonstrates that scalable, operationally efficient health technology can be built with minimal infrastructure burden. However, consolidating this promise requires transition to larger samples, longitudinal observation, and field testing under heterogeneous operational conditions, consistent with methodological recommendations in the literature for integrating EMA into practice while maximizing ecological validity and clinical utility without compromising information protection (Mohr et al., 2013; Conrad, 2024).
4.2 Conclusion
This research designed and developed a digital platform based on Ecological Momentary Assessment (EMA) for therapeutic follow-up, comprising a cross-platform mobile application for patients (Flutter/Dart; Lovrić et al., 2023) and a web dashboard for therapists (Next.js/React/TypeScript; Jha, 2025; Jones, 2025), supported by a serverless cloud architecture with authentication, role-based access control, and backend validations. Based on pilot-phase results with SUS scores of 89.38 for the patient application and 88.12 for the therapist dashboard, alongside qualitative evidence, the general objective of enabling continuous, real-time, user-centered monitoring to improve therapeutic follow-up and patient adherence was achieved. The platform operationalizes EMA in daily routines with minimal user friction, providing clinical decision support through accessible visualizations and automated alert mechanisms.
Regarding specific objectives: (1) EMA’s theoretical and clinical foundations were investigated through comprehensive literature review integrating Cognitive Behavioral Therapy (CBT) principles, EMA/ESM methodologies (Ebner-Priemer & Trull, 2009; Trull & Ebner-Priemer, 2014), and digital intervention models (BIT Model: Mohr et al., 2014; Internet Intervention Model: Ritterband et al., 2009); (2) requirements were elicited with clinical experts (n=4), informing workflow, security, and visualization decisions guided by psychological theory and user-centered principles; (3) a cloud-native, event-driven functional architecture was designed incorporating usability principles (Saparamadu et al., 2021; Norman, 1988), security controls (Mohr et al., 2013; Hu, 2024), and gamification (Firth et al., 2017; Schueller et al., 2017); (4) a functional prototype was developed, capturing, organizing, and visualizing EMA data for patients and therapists with grounding exercise modules (Castilla et al., 2022); and (5) expert feedback was collected through System Usability Scale assessment (Bangor, 2009), guiding future improvements and iterative development. Collectively, these achievements establish a solid technical and methodological foundation for system evolution.
The original contribution of this research resides in the coherent integration of three core axes: (1) EMA as methodological nucleus for in-situ, real-time recording, operationalizing principles validated in clinical research (Stone & Shiffman, 1994; Ebner-Priemer & Trull, 2009); (2) actionable clinical visualization operationalizing the “overview, zoom/filter, details-on-demand” principle (Shneiderman, 2025) to support therapist decision-making through information visualization techniques (Kaya & Epps, 2004); and (3) an explicit security model based on least-privilege principles, declarative rules, and Cloud Functions validations implemented on reproducible serverless infrastructure (Nyabuto, 2024; Cloud Firestore, 2025). This combination offers a lightweight, scalable, and secure solution, particularly relevant for contexts requiring economically and operationally viable mental health digital solutions (Runyan et al., 2013; Kazdin & Blase, 2011). The platform demonstrates that integration of validated psychological methodology (EMA), appropriate technical architecture (serverless, cloud-native, event-driven), and user-centered design principles (Saparamadu et al., 2021) can create an effective tool for therapeutic monitoring and clinical decision support, addressing the documented gap in evidence-based digital mental health tools in Latin America and beyond (Donker et al., 2013).
Given the small pilot sample and non-production evaluation environment, inferences must be considered tentative. Planned continuations include expanding sample size and profile diversity to enhance generalizability, conducting longitudinal studies of adherence and intermediate clinical outcomes while monitoring measurement reactivity, and performing production-environment testing for performance and accessibility metrics. The platform’s theoretical foundation in evidence-based psychological principles (CBT, EMA), user-centered implementation (UCD), and cloud-native architecture (Kratzke & Quint, 2017) position it favorably for clinical application and further research. Additionally, implementation in Latin American healthcare contexts would test cultural adaptability and address regional inequities in access to validated digital mental health solutions.
In conclusion, the MindBloom platform demonstrates technical viability and user acceptability for EMA-based therapeutic follow-up. Its theoretically grounded design, integrating validated psychological methodology (EMA: Ebner-Priemer & Trull, 2009), evidence-based intervention models (BIT Model, Internet Intervention Model), user-centered approach (UCD: Saparamadu et al., 2021), and cloud-native infrastructure (Kratzke & Quint, 2017), contributes concretely to digital mental health technology development. The platform has the potential to improve continuous monitoring and support timely clinical decision-making in real-world settings, particularly in the Latin American context where access gaps and the need for scalable, culturally relevant solutions persist (Meglio et al., 2022; Inostroza et al., 2024). The platform addresses a documented gap between evidence-based psychotherapeutic interventions and practical digital tools, offering a foundation for expanding access to therapeutic monitoring across diverse populations and healthcare settings. Future studies should prioritize longitudinal validation, cross-cultural adaptation, and field testing to consolidate clinical utility and support broader implementation in diverse healthcare systems.
5.
Acknowledgments and Funding
The author expresses profound gratitude to her advisor, Eng. Patricia Ortega Chasi, for her guidance, patience, and academic commitment throughout this research process. Special thanks are extended to Eng. María Inés Acosta for her unconditional support and warmth during this graduation process. Recognition is also given to the Department of Psychology of Universidad del Azuay for its institutional support and for providing the necessary resources and accompaniment to carry out this work. The author acknowledges the four clinical psychology experts who participated in requirements elicitation sessions, contributing their valuable time, knowledge, and recommendations to shape the functional and non-functional specifications of the MindBloom platform. Additionally, thanks are due to the eight volunteer participants (four patients and four therapists) who participated in the pilot usability validation, offering their honest feedback and engagement essential for assessing the platform’s user experience. Finally, sincere appreciation is extended to all colleagues, mentors, and individuals who contributed through discussion, review, and support during the development and completion of this research.
Funding
This research was conducted as a thesis project within the academic framework of Universidad del Azuay and was not supported by external grants or specific funding sources. The development of the MindBloom platform was carried out using open-source technologies (Flutter, Next.js, Firebase free tier during development) and leveraged the institutional resources available through the university’s computer science and psychology departments. No commercial funding or industry sponsorship was involved in the design, development, or evaluation phases of this study.
Conflicts of Interest
The author declares no conflicts of interest related to this research. The MindBloom platform was developed exclusively for research and educational purposes within the academic context. No commercial development, intellectual property claims, or proprietary arrangements are associated with this work. All data and materials used in this study were handled according to institutional ethical protocols and research integrity standards.
References
Aguilera, A., & Muench, F. (2012). There’s an app for that: Information technology applications for cognitive behavioral practitioners. The Behavior Therapist, 35(4), 65-73.
Bangor, A. (2009). Determining what individual SUS scores mean: Adding an adjective rating scale. Journal of Usability Studies, 4(3), 114-123.
Ben-Zeev, D., Schueller, S. M., Begale, M., Duffecy, J., Kane, J. M., & Mohr, D. C. (2015). Strategies for mHealth research: Lessons from 3 mobile intervention studies. Administration and Policy in Mental Health and Mental Health Services Research, 42(2), 157-167. https://doi.org/10.1007/s10488-014-0556-2
Brito, C. H., Vicente, P. B., Brito, C. H., & Vicente, P. B. (2018). Realidad virtual y sus aplicaciones en trastornos mentales: Una revisión. Revista Chilena de Neuro-Psiquiatría, 56(2), 127-135.
https://doi.org/10.4067/s0717-92272018000200127
Brito, G., Terra, R., & Valente, M. T. (2018). Monorepos: A multivocal literature review (arXiv:1810.09477). arXiv. https://doi.org/10.48550/arXiv.1810.09477
Castilla, D., Navarro-Haro, M. V., Suso-Ribera, C., Díaz-García, A., Zaragoza, I., & García-Palacios, A. (2022). Ecological momentary intervention to enhance emotion regulation in healthcare workers via smartphone: A randomized controlled trial protocol. BMC Psychiatry, 22, 164.
https://doi.org/10.1186/s12888-022-03800-x
Castillo Zárate, C. A. (2022). Niveles de estrés asociado a estrategias de regulación emocional interpersonal e intrapersonal en estudiantes universitarios durante el período de exámenes: Un estudio de evaluación ecológica momentánea (EMA) [Master’s thesis]. Universidad del Rosario.
http://hdl.handle.net/1992/64370
Christensen, H., Griffiths, K. M., & Farrer, L. (2009). Adherence in internet interventions for anxiety and depression. Journal of Medical Internet Research, 11(2), e13. https://doi.org/10.2196/jmir.1194
Cloud Firestore. (2025). Store and sync app data at global scale. Firebase. Retrieved from
https://firebase.google.com/products/firestore
Colombo, D., Fernández-Álvarez, J., Patané, A., Semonella, M., Kwiatkowska, M., García-Palacios, A., Cipresso, P., Riva, G., & Botella, C. (2019). Current state and future directions of technology-based ecological momentary assessment and intervention for major depressive disorder: A systematic review. Journal of Clinical Medicine, 8(4), 465.
https://doi.org/10.3390/jcm8040465
Conrad, J. A. (2024). Digitization and its discontents: The promise and limitations of digital mental health interventions. Journal of Contemporary Psychotherapy, 54(3), 209-215.
https://doi.org/10.1007/s10879-024-09620-2
Crochet, T. (2020, January 6). React—Making Recharts easy to use. ForePaaS. Retrieved from https://medium.com/forepaas/react-making-recharts-easy-to-use-e3d99d0641ba
Donker, T., Petrie, K., Proudfoot, J., Clarke, J., Birch, M.-R., & Christensen, H. (2013). Smartphones for smarter delivery of mental health programs: A systematic review. Journal of Medical Internet Research, 15(11), e247. https://doi.org/10.2196/jmir.2791
Ebner-Priemer, U. W., & Trull, T. J. (2009). Ecological momentary assessment of mood disorders and mood dysregulation. Psychological Assessment, 21(4), 463-475. https://doi.org/10.1037/a0017075
Feng, K. J. K., Li, T. W., & Zhang, A. X. (2023). Understanding collaborative practices and tools of professional UX practitioners in software organizations. Proceedings of the 2023 CHI Conference on Human Factors in Computing Systems, 1-20.
https://doi.org/10.1145/3544548.3581273
Firth, J., Torous, J., Nicholas, J., Carney, R., Pratap, A., Rosenbaum, S., & Sarris, J. (2017). The efficacy of smartphone-based mental health interventions for depressive symptoms: A meta-analysis of randomized controlled trials. World Psychiatry, 16(3), 287-298. https://doi.org/10.1002/wps.20472
Garcia-Palacios, A., Herrero, R., Vizcaíno, Y., Belmonte, M. A., Castilla, D., Molinari, G., Baños, R. M., & Botella, C. (2015). Integrating virtual reality with activity management for the treatment of fibromyalgia: Acceptability and preliminary efficacy. The Clinical Journal of Pain, 31(6), 564-572.
https://doi.org/10.1097/AJP.0000000000000196
Heron, K. E., & Smyth, J. M. (2010). Ecological momentary interventions: Incorporating mobile technology into psychosocial and health behaviour treatments. British Journal of Health Psychology, 15(1), 1-39.
https://doi.org/10.1348/135910709X466063
Hu, V. (2024). Access control on NoSQL databases (NIST Internal or Interagency Report 8504). National Institute of Standards and Technology.
https://doi.org/10.6028/NIST.IR.8504.ipd
Inostroza, C., Bustos, C., Bühring, V., González, L., & Cova, F. (2024). Stress, repetitive negative thinking, and mental health in Chilean university students: An ecological momentary assessment study. Frontiers in Psychology, 15, 1400013.
https://doi.org/10.3389/fpsyg.2024.1400013
Jha, V. (2025). Building dynamic web applications using ReactJS. Independently Published.
Jones, L. (2025). Mastering TypeScript for large-scale applications: Unlock the secrets of expert-level skills. Independently Published.
Kaya, N., & Epps, H. H. (2004). Relationship between color and emotion: A study of college students. College Student Journal, 38(3), 396-405.
Kazdin, A. E., & Blase, S. L. (2011). Rebooting psychotherapy research and practice to reduce the burden of mental illness. Perspectives on Psychological Science, 6(1), 21-37. https://doi.org/10.1177/1745691610393527
Khandelwal, V. (2024, August 26). A complete guide to Tailwind CSS: The utility-first CSS framework that’s changing web design. Medium. Retrieved from https://medium.com/@vansh.khandelwal06/a-complete-guide-to-tailwind-css
Khriji, S., Benbelgacem, Y., Chéour, R., Houssaini, D. E., & Kanoun, O. (2022). Design and implementation of a cloud-based event-driven architecture for real-time data processing in wireless sensor networks. The Journal of Supercomputing, 78(3), 3374-3401.
https://doi.org/10.1007/s11227-021-03955-6
Kratzke, N., & Quint, P.-C. (2017). Understanding cloud-native applications after 10 years of cloud computing—A systematic mapping study. Journal of Systems and Software, 126, 1-16.
https://doi.org/10.1016/j.jss.2017.01.001
Lovrić, L., Fischer, M., Röderer, N., & Wünsch, A. (2023). Evaluation of the cross-platform framework Flutter using the example of a cancer counselling app. In Proceedings of the 9th International Conference on Information and Communication Technologies for Ageing Well and E-Health (pp. 135-142).
https://doi.org/10.5220/0011824500003476
Meglio, M., Marasas, S., Fernández Alvarez, J., Gomez, B., & Garcia, F. (2022). Implementación de una evaluación ecológica momentánea (EMA) en la investigación en psicoterapia: Un enfoque cualitativo. In XIV Congreso Internacional de Investigación y Práctica Profesional en Psicología. AACADEMICA.
https://www.aacademica.org/000-084/695
Mengelkoch, S., Moriarity, D. P., Novak, A. M., Snyder, M. P., Slavich, G. M., & Lev-Ari, S. (2023). Using ecological momentary assessments to study how daily fluctuations in psychological states impact stress, well-being, and health. Journal of Clinical Medicine, 13(1), 24. https://doi.org/10.3390/jcm13010024
Mohr, D. C., Burns, M. N., Schueller, S. M., Clarke, G., & Klinkman, M. (2013). Behavioral intervention technologies: Evidence review and recommendations for future research in mental health. General Hospital Psychiatry, 35(4), 332-338.
https://doi.org/10.1016/j.genhosppsych.2013.03.008
Mohr, D. C., Schueller, S. M., Montague, E., Burns, M. N., & Rashidi, P. (2014). The behavioral intervention technology model: An integrated conceptual and technological framework for eHealth and mHealth interventions. Journal of Medical Internet Research, 16(6), e3077. https://doi.org/10.2196/jmir.3077
Morris, R. R., Kouddous, K., Kshirsagar, R., & Schueller, S. M. (2018). Towards an artificially empathic conversational agent for mental health applications: System design and user perceptions. Journal of Medical Internet Research, 20(6), e10148.
https://doi.org/10.2196/10148
Moskowitz, D. S., & Young, S. N. (2006). Ecological momentary assessment: What it is and why it is a method of the future in clinical psychopharmacology. Journal of Psychiatry and Neuroscience, 31(1), 13-20.
Muñoz, R. F. (2010). Using evidence-based internet interventions to reduce health disparities worldwide. Journal of Medical Internet Research, 12(5), e60. https://doi.org/10.2196/jmir.1463
Na, H., Hua, Y., Wang, Z., Shen, T., Yu, B., Wang, L., Wang, W., Torous, J., & Chen, L. (2025). A survey of large language models in psychotherapy: Current landscape and future directions (arXiv:2502.11095). arXiv.
https://doi.org/10.48550/arXiv.2502.11095
Norman, D. A. (1988). The design of everyday things. Basic Books.
Nyabuto, G. M. (2024). Architectural review of client-server models. International Journal of Scientific Research and Engineering Trends, 10(1), 139-143.
https://doi.org/10.61137/ijsret.vol.10.issue1.126
Philippe, T. J., Sikder, N., Jackson, A., Koblanski, M. E., Liow, E., Pilarinos, A., & Vasarhelyi, K. (2022). Digital health interventions for delivery of mental health care: Systematic and comprehensive meta-review. JMIR Mental Health, 9(5), e35159.
https://doi.org/10.2196/35159
Proudfoot, J., Clarke, J., Birch, M.-R., Whitton, A. E., Parker, G., Manicavasagar, V., Harrison, V., Christensen, H., & Hadzi-Pavlovic, D. (2013). Impact of a mobile phone and web program on symptom and functional outcomes for people with mild-to-moderate depression, anxiety and stress: A randomised controlled trial. BMC Psychiatry, 13(1), 312.
https://doi.org/10.1186/1471-244X-13-312
Ritterband, L. M., Thorndike, F. P., Cox, D. J., Kovatchev, B. P., & Gonder-Frederick, L. A. (2009). A behavior change model for internet interventions. Annals of Behavioral Medicine, 38(1), 18-27.
https://doi.org/10.1007/s12160-009-9133-4
Runyan, J. D., Steenbergh, T. A., Bainbridge, C., Daugherty, D. A., Oke, L., & Fry, B. N. (2013). A smartphone ecological momentary assessment/intervention ‘app’ for collecting real-time data and promoting self-awareness. PLOS ONE, 8(8), e71325.
https://doi.org/10.1371/journal.pone.0071325
Saparamadu, A. A. D. N. S., Fernando, P., Zeng, P., Teo, H., Goh, A., Lee, J. M. Y., & Lam, C. W. L. (2021). User-centered design process of an mHealth app for health professionals: Case study. JMIR mHealth and uHealth, 9(3), e18079. https://doi.org/10.2196/18079
Schueller, S. M., Aguilera, A., & Mohr, D. C. (2017). Ecological momentary interventions for depression and anxiety. Depression and Anxiety, 34(6), 540-545.
https://doi.org/10.1002/da.22649
Shneiderman, B. (2025). The eyes have it: A task by data type taxonomy for information visualizations. In Proceedings of the IEEE Symposium on Visual Languages.
Stone, A. A., & Shiffman, S. (1994). Ecological momentary assessment (EMA) in behavioral medicine. Annals of Behavioral Medicine, 16(3), 199-202. https://doi.org/10.1093/abm/16.3.199
Trull, T. J., & Ebner-Priemer, U. (2014). The role of ambulatory assessment in psychological science. Current Directions in Psychological Science, 23(6), 466-470. https://doi.org/10.1177/0963721414550706
van Os, J., Verhagen, S., Marsman, A., Peeters, F., Bak, M., Marcelis, M., Drukker, M., Reininghaus, U., Jacobs, N., Lataster, T., Simons, C., Lousberg, R., Gülöksüz, S., Leue, C., Groot, P. C., Viechtbauer, W., & Delespaul, P. (2017). The experience sampling method as an mHealth tool to support self-monitoring, self-insight, and personalized health care in clinical practice. Depression and Anxiety, 34(6), 481-493.
https://doi.org/10.1002/da.22647
Wenze, S. J., & Miller, I. W. (2010). Use of ecological momentary assessment in mood disorders research. Clinical Psychology Review, 30(6), 794-804.
https://doi.org/10.1016/j.cpr.2010.06.007